
手軽に始められる
フォームテンプレート

 テンプレート一覧に戻る
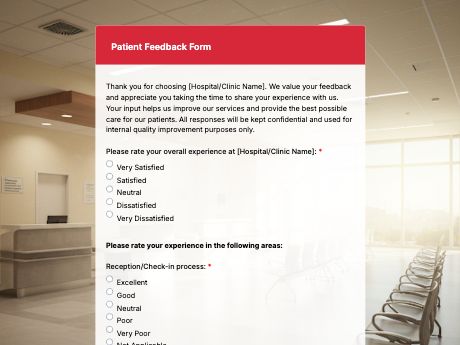
Patient Feedback Form Template for Clinics and Hospitals
Collect and measure the quality of your healthcare service with an online patient feedback form template. Let your patients share their experiences and enhance your service without compromising data confidentiality.
カテゴリー:
フィードバックフォーム
テンプレートを使用
お気に入りに追加
共有
タグ/カテゴリ: フィードバックフォーム
フィールド
SINGLE CHOICE
Please rate your overall experience at [Hospital/Clinic Name]:, Reception/Check-in process:, Waiting time:, Cleanliness of the facility:, Courtesy and professionalism of staff (Receptionists, Nurses, Doctors, etc.), Communication with your doctor (Explanation of diagnosis, treatment options, etc.), Quality of medical care received, Quality of medical care received, Clarity of discharge instructions (if applicable), Billing process, Overall comfort of the facility, Would you recommend [Hospital/Clinic Name] to your friends and family?
LONG TEXT
What did you appreciate most about your visit? (e.g., specific staff members, services, or aspects of your care), What areas could we improve?, Did you encounter any problems during your visit? If so, please describe them., If you answered no to the previous question, why?
DATE
Start Date & End Date
最先端のQR Form Generator Online
最新情報を入手
ニュースレターに登録して、プロモーション、最新情報、ヒントをいち早く入手しましょう
コミュニティに参加する


© 2026 QR Form Generator. All rights reserved.